Revisiting our beliefs about Fluid Resuscitation: An N=1 Podcast. #FOAMed, #FOAMcc

So if you keep abreast of the fluid literature, you’ll note that more and more logical voices are bringing up very, very valid points against the powerful cultural backdrop of aggressive fluid resuscitation in various pathologies. Paul Marik’s recent publication, a great SMACC 2013 lecture by John Myburgh, not to mention several studies and analyses (VISEP, SOAP) illustrating consequences of overzealous fluid resuscitation. On the other side of the fence, you have the guidelines of various associations proclaiming loudly that fluids are “critically important” that there is a need to be “aggressive” and “generous.”  However, scratch a little beneath the surface and find…very little besides opinion and history. Zip. Nothing.

So my aim isn’t to make anyone stop giving fluids, but instead to treat fluids as any other therapy. Carefully given and assessed rather than in hyped-up frenzy.

I invite every physician reading or listening to, for a few minutes, put pre-concieved notions aside and approach the problem from a neutral and educated point of view, and come to your own conclusion, as unbiased as possible.

So here is my little podcast.


cheers


Philippe


ps just as I was uploading, checked my twitter and noted a great addition to the body of analysis by Josh Farkas, check it out:

http://www.pulmcrit.org/2014/08/the-myth-of-large-volume-resuscitation.html?m=1

Another plea. Please stop embarassing us. #FOAMed, #FOAMcc.

Despite physiological rationale, common sense, and a JAMA article now almost 2 years old, I still sadly see most of my internal medicine colleagues still routinely reaching for (ab)normal saline.

Its embarrassing.

I genuinely feel bad recommending other fluids in consultations, or in the room of a crashing patient asking the nurse to stop the bolus of NS and change it at least to RL, because it is such a ‘basic’ intervention. Prior to the JAMA article, I mostly gave people the benefit of the doubt. Resuscitation isn’t everyone’s field of interest, nor is physiology, so I didn’t feel that necessarily everyone HAD to know this and ascribe to it. I do understand the 10 year time of knowledge translation, but that’s why #FOAMed exists, to try to cut that down.

So please, unless your goal is specifically chloride repletion, take a deep breath and release your grasp on habit and tradition, and embrace physiology (at least to some degree) and stop using NS as a volume expander whether in bolus or in infusion. RL or plasmalyte – although not physiological, at least not as biochemically disturbing as is 0.9% NaCl.

Having said that, let’s keep in mind that human fluid is colloid, whether it includes a cellular suspension (blood, lymph) or not (interstitial fluid), made of a varying mix of proteins, electrolytes, hormones and everything else we know – and some we don’t – floating around. There is no compartment that contains a crystalloid solution.

I’m quite aware that no meta-analysis has shown that colloids are superior, but it likely is just a matter of the right colloid. Resuscitating with crystalloids is kinda like throwing a bucketful of water at an empty bucket across the room. 70-80% spill, if you’re lucky. And the cleanup may be more costly than a few sweeps of the mop. This is evidence based (SOAP, VASST, etc..).

So a plea to all, spread the word. Its a simple switch. Boycott hyperchloremic acidosis at least.

For more details, here’s a link to my earlier post on NS: http://wp.me/p1avUV-5x

cheers


Philippe

The N=1 concept. #FOAMed, #FOAMcc

First of all, happy holidays to all and happy new year!

Following a few requests, I’m gonna put up a few words about the N=1 concept, as I think it comes up in every single therapeutic and diagnostic strategy.

We do not treat a thousand, a hundred or even ten patients at a time.  As clinicians, we deal with a single patient, with a certain pathology, and his own, unique physiological pattern of response to that pathology.

In a medical utopia, we would be able to have a precise biophysiological profile of our patient – probably including parameters that either don’t yet exist, or are on the verge of being found or invented.  We would know, for instance, the degree of glycocalyx damage, the nature of this damage, the degree of subsequent capillary leak, the specific inflammatory cytokine pattern, and thus be able to use a potential combination of agonists and antagonists to favor healing, and tailor fluid therapy to the “just right” amount, avoiding both under-resuscitation and tissue edema. This would be similar to antibiotic sensitivity testing. Who, in this century so far, would deliberately not order sensitivities, instead satisfying themselves with a positive result and happy with empiric therapy?

Just in terms of biological variability, it is impossible to believe that all patients would respond best to a single goal or therapy. How can an MAP of 65 be as good for a septic hypertensive patient as it is for a young septic woman who normally walks around with an SBP of 110? Not that I don’t use that number myself most of the time, but certainly food for thought, and something to keep in mind when treating either of those “types” of patients…

And the answer to the N=1 riddle isn’t just subgroup analysis. The questions have to be answered in prospective fashion, built into the study design. Not easy work, and especially since we don’t yet even know what the key variables/questions are… But personally, as mentioned in an earlier post, I do now suspect that the ubiquitous glycocalyx holds some of those answers.

Let’s look at the whole fluid debate through the N=1 lens: it makes no sense whatsoever to debate crystalloids versus colloids. This negates thinking and only encourages near-religious fervour amidst both camps. Rather, look at your patient. Is he truly dehydrated/volume depleted or just volume responsive on the basis of vasodilation. If we want to restore the ICF and the interstitium, then crystalloids are probably better, but if we want to restore effective circulatory volume, then some measure of colloid may help avoid excessive edema, though even this can be debated. Even more important is the composition of the resuscitation fluid. Much as we adjust our TPN, we should probably design our resuscitation fluids, rather than only using Ringer’s Lactate (I say only just to drive the point that NS should not be used as a resuscitation fluid, unless repleting chloride is specifically necessary).

Now this may sound like a rant against large trials, but it isn’t. Absolutely invaluable information can be derived from these, it is just a matter of thinking how that information can benefit the one patient you have in front of you. And this isn’t easy. You have to put together your history, physical exam, bedside ultrasound exam and labwork. You can’t just say  “sepsis? 2 litres,” or any other such recipe (aka protocols).

ok, enough for a january 1st!


Love to hear what anyone thinks!


Philippe


The Glycocalyx: an overview for the clinician. #FOAMed, #FOAMcc

Ok, so I’d had a couple of glimpses at articles in the past few years which referred to the glycocalyx, but, in truth, I tend to read most of the “bench” studies a little, well…quickly.  So basically, when I listened to Paul’s (Marik) recent lecture at Scott’s (Weingart, emcrit.org) New York Sepsis Collaborative, I started to dig a little…and whoa! And then of course, then now-famous expose by John (Doe?) on EmCrit continued to convince me that this is definitely something I need to pay attention to! Its not like there hasn’t already been a high level of scrutiny of the glycocalyx in the field of sepsis.  Google it. Its like a whole new world. It just hasn’t yet translated into an effective therapy, but nor has it seemed to spread into general awareness, and it seems like it’s high time it does, since it is the interface between the blood and the body – a “blood-body barrier” of sorts.

So here we go, a crash course on the glycocalyx for the clinician in the trenches…

The existence of an acellular layer lining the endothelium was described by Luft some 40 years ago (1), and in the last decade has come under scrutiny for its role in various pathophysiological states, which seems to be quite exhaustive. This has not yet translated into diagnostic or therapeutic interventions, but it seems its properties, or at least those we are currently aware of, should be kept in mind when we are faced with therapeutic choices given that some of these may have an effect on the glycocalyx.

Its existence was deduced due to the lower capillary hematocrit – meaning that the hematocrit in the capillaries, adjusted for the luminal volume, is lower than that of the large or medium vessels, implying an area where there are no red cells. This was confirmed by electron microscopy and found to be a gel-like epithelial lining which acts as an interface between the blood and the endothelial cells, of a thickness of about 0.5 um at the level of tha capillaries, and thicker in the larger vessels.

So what is it made of? Its is essentially a meshwork of glycoproteins and proteoglycans, anchored to the epithelial cells, in which many soluble molecules are enmeshed. It is important to note that there is a dynamic equilibrium between this layer and the adjacent flowing blood, which will affect the thickness and composition of the glycocalyx. The layer seems to be vulnerable to both enzymatic degradation as well as to shear forces, in variable degrees. Enzymatic removal of components seems to radically alter properties, pointing to a strong synergistic effect of the various components. It is a constantly shedding and regenerating structure.

glycocalyx em pic

EM view of the glycocalyx (reproduced with authors’ permission from Reitsma et al.)

glycocalix pic2

(reproduced with authors’ permission from Reitsma et al.)

Major components:

– Proteoglycans (protein core with chains of glycosaminoglycans) are the “backbone” of the glycocalyx, and consist of syndecans, glipicans, mimecan, perlecans and biglycans.

– Glycosaminoglycans (linear disaccharide polymers of a uronic acid and a hexosamine) are predominantly heparan sulfate (50-90%), then dermatan sulfate, chondroitin sulfate, keratan sulfate and hyaluronan (or hyaluronic acid).

– Glycoproteins are also part of the “backbone” structure and the main types are the endothelial cell adhesion molecules ( -cams, which are selectins, integrins and immunoglobulins) and components of the fibrin/coagulation system.  E- and P-selectins as well as others are involved in leukocyte-endothelial interaction and diapedesis, an important aspect of local inflammation.

– Soluble components are also embedded in the glycocalyx such as proteins and soluble proteoglycans and are important in preserving the charge of the layer and play critical roles in functionality.

Function of the glycocalyx (as far as we know…)

a. gatekeeper

It is a key determinant of vascular permeability. Partial enzymatic removal without damage to the endothelial cells themselves result in a radical change in permeability in aminal models. Charge, size and steric hindrance affect permeability. The glycocalyx has a highly net negative charge towards the bloodstream – neutralizing this induces an increase in cellular albumin uptake.

Weinbaum introduced a new model integrating the glycocalyx in the classical (but now outdated and disproven) Starling model of microvascular fluid exchange. The revised Starling principle stresses the importance of an intact glycocalyx.

Its role with cellular elements is interesting, as it contains key elements for interaction (-CAMs) but at the same time physically prevents direct interaction between cells (WBC, RBC, plt) and the endothelium. This clearly points to a pivotal role in controlling the interaction. Damage by various methods consistently shows increased neutrophil-endothelial interaction (often termed “leukocyte rolling”). It isn’t much of a stretch to see how the glycocalyx will thus be involved in the control of local inflammation.

b. mechanotransduction

The glycocalyx provides mechanical protection from shear stress to the endothelium.  Increased shear leads to upregulation of synthesis, and correspondingly, thicker glycocalyx is found in high shear areas.

c. microenvironment

Receptor binding, local growth and repair, and vasculoprotection. For instance, ATIII is bound to the glycocalyx (inhibits procoagulants), as well as superoxide dismutase, key in reducing oxidative stress and maintaining MO availability.

Clinical implications…

Now this is the real question.  I think that the first step is acknowledging the presence and importance of the glycocalyx, and trying to discern which of our interventions may have an impact.  It is quite clear that enzymes, cytokines and ischemia/reperfusion all damage the glycocalyx and result in increased cellular interaction and permeability. In a way this can explain the entire “SIRS” spectrum with diffuse damage resulting from an insult that may or may not be infectious in origin. Obviously, we know to avoid anything that might cause the above.

I think we can divide our interventions into two types:

a. those that inherently disrupt the glycocalyx –

b. those that secondarily disrupt it via another mediator – eg over-resuscitation and ANP/BNP (John’s “evil twins”) elevation causing breakdown.

Here are some interesting facts, in no particular order of importance:

a. in acute hyperglycemia and in type I diabetes, there is significant loss of glycocalyx volume.

Nieuwdorp M, van Haeften TW, Gouverneur MC, Mooij HL, van Lieshout MH, Levi M, Meijers JC, Holleman F, Hoekstra JB, Vink H, Kastelein JJ, Stroes ES (2006) Loss of endothelial glycocalyx during acute hyperglycemia coincides with endothelial dysfunction and coagulation activation in vivo. Diabetes 55:480–486.

Nieuwdorp M, Mooij HL, Kroon J, Atasever B, Spaan JA, Ince C, Holleman F, Diamant M, Heine RJ, Hoekstra JB, Kastelein JJ, Stroes ES, Vink H (2006) Endothelial glycocalyx damage coincides with microalbuminuria in type 1 diabetes. Diabetes 55:1127–1132

b. high fat/high cholesterol diet and high LDL levels disrupt the glycocalyx. The co-infusion of superoxide dysmutase and catalase with ox-LDL abolishes the glycocalyx shedding found with ox-LDL infusion only. (not exactly a big surprise, but certainly brings up a therapeutic possibility in acute coronary events, especially NSTEMIs…)

Vink H, Constantinescu AA, Spaan JA (2000) Oxidized lipoproteins degrade the endothelial surface layer: implications for platelet–endothelial cell adhesion. Circulation 101:1500–1502

van den Berg BM, Spaan JA, Rolf TM, Vink H (2006) Atherogenic region and diet diminish glycocalyx dimension and increase intima-to-media ratios at murine carotid artery bifurcation. Am J Physiol Heart Circ Physiol 290:H915–H920

c. hydrocortisone and antithrombin prevent TNF-a induced shedding of the glycocalyx. (we never really knew how steroids help in sepsis; ATIII trials failed, but were they designed with glycocalyx-sparing in mind…?)

Daniel Chappell MD, Klaus Hofmann-Kiefer, Matthias Jacob, Markus Rehm, Josef Briegel, Ulrich Welsch, Peter Conzen, Bernhard F. Becker TNF-α induced shedding of the endothelial glycocalyx is prevented by hydrocortisone and antithrombin Basic Research in Cardiology, January 2009, Volume 104, Issue 1, pp 78-89

 d. endotoxemia damages the pulmonary vascular endothelium and results in ALI (now the neutrophils can attach and activate inflammation…)

Eric P Schmidt, Yimu Yang, William J Janssen, Aneta Gandjeva, Mario J Perez, Lea Barthel, Rachel L Zemans, Joel C Bowman, Dan E Koyanagi, Zulma X Yunt, Lynelle P Smith, Sara S Cheng, Katherine H Overdier, Kathy R Thompson, Mark W Geraci, Ivor S Douglas, David B Pearse & Rubin M Tuder The pulmonary endothelial glycocalyx regulates neutrophil adhesion and lung injury during experimental sepsis, Nature Medicine 18,1217–1223 (2012)

e. sepsis and major abdominal surgery damage the glycocalyx (a good example of common pathway pathophysiology…)

Jochen Steppan, M.D., Stefan Hofer, M.D., Benjamin Funke, M.D., Thorsten Brenner, M.D., Michael Henrich, M.D., Ph.D., Eike Martin, M.D.,Jürgen Weitz, M.D., Ursula Hofmann, M.D., Markus A. Weigand, M.D.Sepsis and Major Abdominal Surgery Lead to Flaking of the Endothelial Glycocalix Journal of Surgical Research Volume 165, Issue 1 ,Pages 136-141, January 2011

f. molecules (eg Slit2N,  good old aPC) that enhance or preserve barrier function have shown some success in animal models. (the key might be to using a bunch of them at once, not one of them vs placebo)

N. R. London, W. Zhu, F. A. Bozza, M. C. Smith, D. M. Greif, L. K. Sorensen, L. Chen, Y. Kaminoh, A. C. Chan, S. F. Passi, C. W. Day, D. L. Barnard, G. A. Zimmerman, M. A. Krasnow, D. Y. Li, Targeting Robo4-dependent Slit signaling to survive the cytokine storm in sepsis and infl uenza. Sci. Transl. Med. 2, 23ra19 (2010).

…and this is just the tip of the iceberg. Seriously, google it…

Conclusion:

For now, it is difficult to make any hard recommendations, but it has certainly made me pause to regroup and re-strategize. I think the critical thing is to reframe our thinking and redesign our approach to be a glycocalyx-sparing therapy.

In sepsis therapy, so many molecules have failed, but little emphasis so far has been on targeting the glycocalyx, and in all likelihood, the key is not in finding the “magic bullet” but rather using multiple interventions to bolster it. One could think of this as the sepsis “chain-of-survival”, and now that we can see the complexity of the glycocalyx, it is easy to understand how no one therapy, even if it did do its job, would succeed in preventing the degradation of the other links in the chain, and fail.  In all likelihood, a successful strategy will probably involve the following:

1. fancy molecules to prevent glycocalyx damage.

2. fluid choices which are glycocalyx-friendly.

3. fluid in just the right amount (not by macro/volume-responsiveness but by micro/glycocalyx management).

4. rapid diagnosis/abx/source control, etc, all the good stuff we know about.

5. preventing hyperglycemia.

A trial like that would be a monumental undertaking. I can only hope someone does it.

My next step, as a guy in the bedside trenches and not at the bench, after gaining a modicum of understanding on the topic, will be to delve deeper into the effects of currently available fluids on the glycocalyx.  Look for a post on that in the next weeks.  As a starter, everyone should review Woodcock & Woodcock’s excellent clinical review.

And if anyone has any amazing information to share, please do!!! That’s what #FOAMed is for!!!

Suggested viewing/reading:

Woodcock and Woodcock, BJA 2012,  http://bja.oxfordjournals.org/content/early/2012/01/29/bja.aer515.full.pdf+html

Broken Barriers: A New Take on Sepsis Pathogenesis Neil M. Goldenberg,1* Benjamin E. Steinberg,1* Arthur S. Slutsky,2,3,4 Warren L. Lee2,4 Science Translational Medicine, 22 June 2011 Vol 3 Issue 88 88ps25

Click to access Science_Translational_Medicine_2011_Pathogenesis_of_Sepsis.pdf

a great article on understanding the glycocalyx in sepsis by a U of T gang!

emcrit:

http://emcrit.org/blogpost/best-fluids-comment-ever/

http://emcrit.org/podcasts/fluids-severe-sepsis/

http://emcrit.org/podcasts/paul-marik-fluids-sepsis/

all must-listen/watch material!

other refs.

Luft JH (1966) Fine structures of capillary and endocapillary layer as revealed by ruthenium red. Fed Proc 25:1773-1783

Reitsma et al, The endothelial glycocalyx: composition, functions, and visualization, Eur J Physiol (2007) 454:345–359

Zhang X, Adamson RH, Curry FR, Weinbaum S (2006) A 1-D model to explore the effects of tissue loading and tissue concentration gradients in the revised Starling principle. Am J Physiol Heart Circ Physiol 291:H2950–H2964

Enough with the “Normal” Saline!!!!! #FOAMed, #FOAMcc

Enough with the “Normal” Saline!
So its been about a year since a JAMA article (http://jama.jamanetwork.com/article.aspx?articleid=1383234) finally showed that the downside of 0.9% saline isn’t just theoretical, but has some associated clinical morbidity (bad for the kidneys!).  Sadly enough, it still seems to be the routine fluid used for boluses. Whether the ER, hospitalist or intensivist, residents, students…it seems people are reluctant to let go.
Today, rounding in the ICU, I was changing an order for a bolus from another doc from NS to RL, and a nurse asked me why.  I gave her a capsule summary and she was in disbelief.  “Come on Phil, they wouldn’t call it normal saline if it wasn’t!”
I’m an internist by training, so naturally I grew up using NS, since that’s what all the attendings and residents used around me.  Ringer‘s was the stuff the surgeons used, so well, I guess it had to be wrong…no?
So forward to 2001 and John Kellum‘s lecture on acid-base I’ve previously mentioned, and my exploring Stewart’s Physicochemical Approach, and wait, I look at the back of a bag of NS, and find out, much to my dismay, that the stuff I’ve been using like holy water has a pH of 5.6.  And who have I been giving liters and liters of this stuff to?  Yup, mostly patients with acidosis. Hmmm. Interesting. So although I don’t necessarily advocate correcting metabolic acidosis for the sake of doing so (see my previous post on bicarb), I’m not a proponent of worsening acidosis either, even if by another mechanism.
I think there are a number of factors that have resulted in this situation.  For starters, there is the issue of false advertising – the “normal saline” monicker has been influencing subliminal thought for decades (think Malcolm Gladwell thin-slicing), making physicians feel they are giving and inherently “good” substance.  Then there’s the whole tribalism thing with the surgeons vs non-surgeons making all the non-surgeons polarize away from RL (not that RL is perfect, just a bit better, and certainly closer to “normal”). Finally, there’s this sad, sad factor that makes people, even (or maybe even more) smart people reluctant to accept that they have been doing something wrong (or, for those who are offended right now, not ideal) for a long time (I sure was) and prefer to fight it and rationalize it for a few more years until, eventually, the evidence becomes overwhelming or the changing of the guard has fully taken place.
I think what we should be hanging on to is not a drug or a fluid but rather what we learned in the first couple of years of med school: physiology.  Now mind you, at that point we (or most of us) didn’t have a clue how to use it for anything more that answering multiple choice questions, but at some point, we have to go back to it and realize that is what we should be basing our assessment of our therapeutic acts and decisions.
So…if I have a situation where I am low on chloride, I might want to use NS. But otherwise, let try to give something whose composition is a bit closer to our own than NS is.  So, for my students and residents, don’t let me see you prescribing boluses of NS.  If you really, really need to, wait until your next rotation please.
thanks!
Philippe
ps for a great review of the original aritcle, please see Matt’s on PulmCCM at :
Reply:  by Marco Vergano
Totally agree!
I have been struggling for years with the bad habit of some of my colleagues prescribing NS as the most harmless and physiologic replacement fluid. Here in Italy we don’t have such a clear separation between internists and surgeons about NS/RL choice: the bad habit of easily prescribing NS is ubiquitous.
Given the results you mentioned about the increased incidence of renal failure with NS, I am wondering if the ban on ALL starch solutions would have been necessary after the introduction of new balanced starch/electrolyte solutions.
What I really don’t like about RL is that it’s not only hypotonic, but also low in sodium. In our ICU we often have many ‘neuro’ patients (trauma or vascular) and sodium variations become a major issue. Also I prefer Ringer’s acetate over lactate on most of the patients who struggle to ‘manage’ their own lactate.
So my favorite solution remains our good old “Elettrolitica reidratante III” (very similar to Plasma-lyte).

NEJM Circulatory Shock Review by Vincent & DeBacker: the sweet and the not-so sweet… #FOAMed, #FOAMcc

So if anyone hasn’t read it, here it is:

Click to access Circulatory%20Shock%20-%20NEJM%202013.pdf

I read the article by critical care icons Dr. Jean-Louis Vincent and Dr. De Backer with interest  as I am always keen to find out what the cutting edge is… So here is my take on their review.

The not-so-sweet:

The inclusion of CVP in the assessment. Ouch. No evidence whatsoever. Evidence for lack of correlation to fluid responsiveness… I wonder if they themselves were cringing a little about including it, particularly form the fact that they just put high vs low rather than commit to a value, which makes me think they realize it’s a bit of a trap. (It reminds me a bit of those night-time orders I still sometimes see which say if u/o < 30 cc/hr give a bolus if CVP under 12 or lasix if over 12.  So basically depending on whether that patient’s head is elevated, or if he’s turned on one side or the other, he may go from “needing fluids” to “needing diuretics”…).

The sweet:

First of all, they obviously did an elegant job on description of shock states, and particularly of highlighting the common-ness of mixed etiology shock.

I like that they admitted that the end-point for fluid resuscitation is “difficult to define.”  Any answer other than that would really speak to non-physiological thinking, as I’ve referred to in prior posts/podcasts.

Dopamine: good job on trying to take it off the shelf for shock. As far as I’m concerned, only useful when you’ve run out of norepinephrine, although there is the odd time when you have a septic AND bradycardic patient where it could come in handy…

Bringing some focus on the microcirculation: no recommendations, but that’s appropriate since there are none to be made yet, but this is where the money is in the future, as far as I’m concerned. Once we figure out how to manage the microcirculation (we do ok with the macro circulation) we might forge ahead. But good to point the finger in that direction.

The super-sweet!

I do (not surprisingly) really, really like the fact that they included ultrasound in their assessment protocol, and emphasizing that focused echocardiography should be done as soon as possible.  Very nice. Finally.

Hopefully, this pushes mainstream ED and critical care physicians to realize they need basic bedside ultrasound skills…


Overall, I think it is a good review, certainly worth the read for trainees. I would like to see focus on re-examining and questioning our approach, which could spur readers to embark on research with a different angle. For instance, why do we assume that we need to fill patients to the point of no longer being fluid responsive in order to avoid vasopressors? Is there any evidence for that? Not that I know of…

But, for having put an emphasis on point-of-care ultrasound, it gets a big round of applause from me!


Philippe

CCUS 2013 Lectures – #FOAMed, #FOAMcc

This past may we had an amazing two day conference, the theme of which was challenging dogmatic practice and myths in acute care medicine.  Many of the lectures are now available to watch on our website at http://www.ccusinstitute.org/e-Store.asp?method=evideos#, you need to be a member to access – which is free, just register.


Lectures on bedside ultrasound, shock, ECMO in the ED, physiology and a lot of really, really good stuff.


We will be adding more in the next weeks!


Thanks!


PR

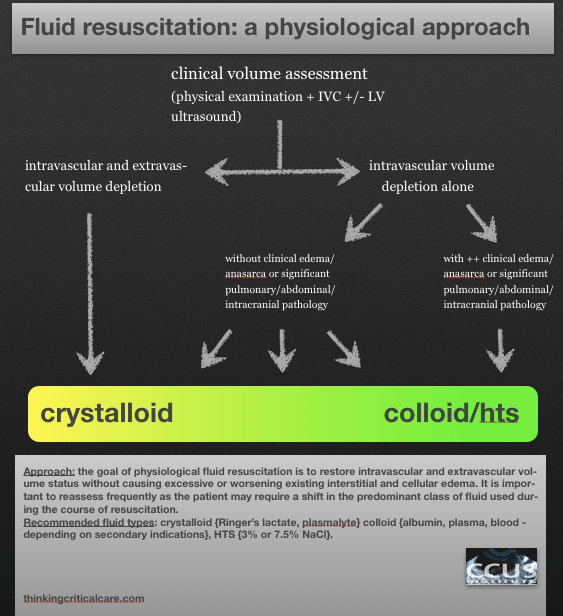
fluid resuscitation: a physiological approach – an N=1 podcast, #FOAMed, #FOAMcc

This is my approach to fluid resuscitation – sorry for the lack of precision which, to me, is actually key.  It would be against the N=1 principle to give out a recipe…but here’s a way to think about it:

Sorry the last bit cut off – my iphone can only email an 8 minute audio clip! Which I wasn’t aware of until today.  Anyway all that was lost at the end was “thanks for listening and I’d really like to hear comments and others’ practices!”

And here’s a disclaimer:  I don’t think this is the be-all and end-all. My resuscitation is a work in progress, both in terms of new fluids coming up, and in terms of identifying subgroups or individuals who would benefit from a different approach, so I’m definitely eager to hear from anyone who does things differently – but physiologically!

Please see Dr. John Myburgh’s excellent review on fluid resus in NEJM sep 26th issue!

Oh and here’s the diagram!

Physiological Fluids

thanks!

Philippe

Bedside Ultrasound Picture Quiz 2 #FOAMed, #FOAMcc

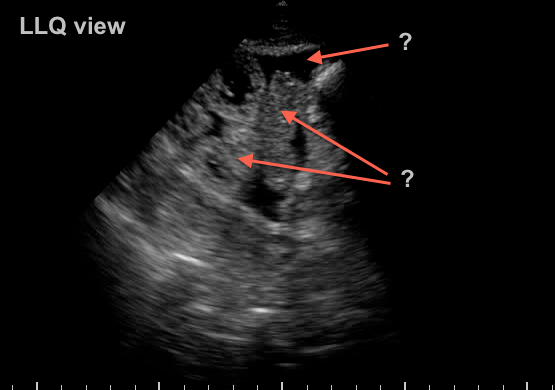
73 yr old woman recovering from septic shock with abdominal distension and difficulty tolerating enteral feeds…


what do you see?

BUPQ2


scroll below for the answer…..


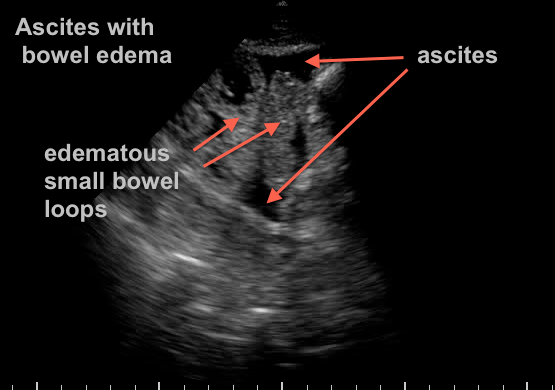
BUPQ2 Answer


Extensive third spacing from resuscitation has resulted in bowel edema and ascites.  Another “benign” effect of massive crystalloid use… A bedside 22g US guided tap confirms benign transudate.

The Ideal Resuscitation Fluid – an N=1 Podcast #FOAMed, #FOAMcc

So here is the first in a series of mini-talks geared towards having us think about fluid resuscitation, which, for those in acute care of almost any type (ER, wards, ICU, anasthesia, surgery, etc…) is part of our daily routine. And that’s exactly what it shouldn’t be, routine. It should be carefully thought out and adapted to each individual clinical situation we’re facing.

So I’ve decided to approach this from a completely different angle, not looking at what we do, what’s available, and see what has been stacked up against what, etc, etc… Instead, I’ve decided to start the discussion from a completely theoretical standpoint and talking about something that doesn’t exist:  The Ideal Resuscitation Fluid.

Please, let me know your thoughts!

Philippe

http://www.ccusinstitute.org

(sorry the last 40 seconds were cut – now the “full” 5 minutes are up!  apologies, I am techno-challenged!)