Blood transfusion and serum S1P levels in Sepsis: a leaky proposition? (Protecting the Glycocalyx Part1) #FOAMed, #FOAMcc

So in my ongoing quest to reframe my resuscitation step-by-step, I’ve been following up on a number of leads regarding the glycocalyx, as previously stated, and John’s reference to this article in a previous comment I feel is highly relevant. So this is it:

Synergistic Effect of Anemia and Red Blood Cells Transfusion on Inflammation and Lung Injury,  Anping Dong, Manjula Sunkara, Manikandan Panchatcharam, Abdel Salous, Samy Selim, Andrew J.Morris, and Susan S. Smyth

Advances in Hematology, Volume 2012, Article ID 924042, 8 pages

http://www.hindawi.com/journals/ah/2012/924042/

S1P (sphingosine-1-phosphate) is a regulator of endothelial permeability and immune function.  Uh-oh, why had I not heard of it? Hmmm…I don’t think it was in Guyton’s or in Harrison’s…and there hasn’t been an RCT about it… Ok, that about explains it.

So here are some factoids about S1P:

–       serum levels correlate with HCT as RBCs serve as an S1P reservoir.

–       anemic patients’ S1P levels are NOT fully replenished by transfusion, especially the older the transfused blood is.

–       In fact, older RBCs may actually remove plasma S1P.

The study:

They basically took mice, and in the first group, bled them (by 20ml/kg) and looked at inflammatory markers, lung permeability and also S1P levels. That’s basically the control group, and they noted that hemorrhage significantly increased inflammatory markers (interesting in and of itself) . They then transfused these mice using wither fresh, S1P-loaded RBCs, or 14-day old RBCs, and, lo and behold, the fresh blood resulted in less inflammation, increased S1P, but most importantly, markedly decreased lung permeability. So clearly, S1P attenuates transfusion associated lung permeability.

In the next group, they injected the mice with LPS following hemorrhage, and found a synergistic effect of blood loss and LPS on inflammation and lung permeability, as could be imagined. Following the LPS, they were transfused with one of four strategies: fresh blood, old blood, fresh blood + S1P or old blood + S1P.  Well, lung permeability still increased in all groups, but least in the fresh blood + S1P, and the old blood + S1P a close second.

Note, interestingly enough, that saline alone (the “control”) also increased lung permeability, highlighting yet again that NS (and probably any crystalloid) is not innocuous…

So here we’re looking at the finer effects of transfusion, and why, against “common-sense” correcting a patient’s hemoglobin level does not seem to help in all situations.  We have understood the aging issue and loss of deformability, but it is time to take a finer look.  We are familiar – at least in concept – with transfusion-associated lung injury or TRALI, but the mechanism remains unclear.

Summary and Take-Home message:

S1P infusions in sepsis?  Maybe someday…

Yes, this is an animal study, and the results cannot be extrapolated directly to humans, but it is food for thought, as John had mentioned.  Certainly at least this should tell us to keep and ear/eye out for human work with S1P, but personally, it will make me even more comfortable in not transfusing my septic patients with hb’s in the low 70’s and maybe even high 60’s (try repeating the cbc, more often than not comes back a couple points higher and you can avoid transfusion), and for those who are a little more aggressive with transfusion, maybe this should make them think twice…

I’ll add what I can dig up on human S1P studies soon.

cheers!

Philippe

The Glycocalyx: an overview for the clinician. #FOAMed, #FOAMcc

Ok, so I’d had a couple of glimpses at articles in the past few years which referred to the glycocalyx, but, in truth, I tend to read most of the “bench” studies a little, well…quickly.  So basically, when I listened to Paul’s (Marik) recent lecture at Scott’s (Weingart, emcrit.org) New York Sepsis Collaborative, I started to dig a little…and whoa! And then of course, then now-famous expose by John (Doe?) on EmCrit continued to convince me that this is definitely something I need to pay attention to! Its not like there hasn’t already been a high level of scrutiny of the glycocalyx in the field of sepsis.  Google it. Its like a whole new world. It just hasn’t yet translated into an effective therapy, but nor has it seemed to spread into general awareness, and it seems like it’s high time it does, since it is the interface between the blood and the body – a “blood-body barrier” of sorts.

So here we go, a crash course on the glycocalyx for the clinician in the trenches…

The existence of an acellular layer lining the endothelium was described by Luft some 40 years ago (1), and in the last decade has come under scrutiny for its role in various pathophysiological states, which seems to be quite exhaustive. This has not yet translated into diagnostic or therapeutic interventions, but it seems its properties, or at least those we are currently aware of, should be kept in mind when we are faced with therapeutic choices given that some of these may have an effect on the glycocalyx.

Its existence was deduced due to the lower capillary hematocrit – meaning that the hematocrit in the capillaries, adjusted for the luminal volume, is lower than that of the large or medium vessels, implying an area where there are no red cells. This was confirmed by electron microscopy and found to be a gel-like epithelial lining which acts as an interface between the blood and the endothelial cells, of a thickness of about 0.5 um at the level of tha capillaries, and thicker in the larger vessels.

So what is it made of? Its is essentially a meshwork of glycoproteins and proteoglycans, anchored to the epithelial cells, in which many soluble molecules are enmeshed. It is important to note that there is a dynamic equilibrium between this layer and the adjacent flowing blood, which will affect the thickness and composition of the glycocalyx. The layer seems to be vulnerable to both enzymatic degradation as well as to shear forces, in variable degrees. Enzymatic removal of components seems to radically alter properties, pointing to a strong synergistic effect of the various components. It is a constantly shedding and regenerating structure.

glycocalyx em pic

EM view of the glycocalyx (reproduced with authors’ permission from Reitsma et al.)

glycocalix pic2

(reproduced with authors’ permission from Reitsma et al.)

Major components:

– Proteoglycans (protein core with chains of glycosaminoglycans) are the “backbone” of the glycocalyx, and consist of syndecans, glipicans, mimecan, perlecans and biglycans.

– Glycosaminoglycans (linear disaccharide polymers of a uronic acid and a hexosamine) are predominantly heparan sulfate (50-90%), then dermatan sulfate, chondroitin sulfate, keratan sulfate and hyaluronan (or hyaluronic acid).

– Glycoproteins are also part of the “backbone” structure and the main types are the endothelial cell adhesion molecules ( -cams, which are selectins, integrins and immunoglobulins) and components of the fibrin/coagulation system.  E- and P-selectins as well as others are involved in leukocyte-endothelial interaction and diapedesis, an important aspect of local inflammation.

– Soluble components are also embedded in the glycocalyx such as proteins and soluble proteoglycans and are important in preserving the charge of the layer and play critical roles in functionality.

Function of the glycocalyx (as far as we know…)

a. gatekeeper

It is a key determinant of vascular permeability. Partial enzymatic removal without damage to the endothelial cells themselves result in a radical change in permeability in aminal models. Charge, size and steric hindrance affect permeability. The glycocalyx has a highly net negative charge towards the bloodstream – neutralizing this induces an increase in cellular albumin uptake.

Weinbaum introduced a new model integrating the glycocalyx in the classical (but now outdated and disproven) Starling model of microvascular fluid exchange. The revised Starling principle stresses the importance of an intact glycocalyx.

Its role with cellular elements is interesting, as it contains key elements for interaction (-CAMs) but at the same time physically prevents direct interaction between cells (WBC, RBC, plt) and the endothelium. This clearly points to a pivotal role in controlling the interaction. Damage by various methods consistently shows increased neutrophil-endothelial interaction (often termed “leukocyte rolling”). It isn’t much of a stretch to see how the glycocalyx will thus be involved in the control of local inflammation.

b. mechanotransduction

The glycocalyx provides mechanical protection from shear stress to the endothelium.  Increased shear leads to upregulation of synthesis, and correspondingly, thicker glycocalyx is found in high shear areas.

c. microenvironment

Receptor binding, local growth and repair, and vasculoprotection. For instance, ATIII is bound to the glycocalyx (inhibits procoagulants), as well as superoxide dismutase, key in reducing oxidative stress and maintaining MO availability.

Clinical implications…

Now this is the real question.  I think that the first step is acknowledging the presence and importance of the glycocalyx, and trying to discern which of our interventions may have an impact.  It is quite clear that enzymes, cytokines and ischemia/reperfusion all damage the glycocalyx and result in increased cellular interaction and permeability. In a way this can explain the entire “SIRS” spectrum with diffuse damage resulting from an insult that may or may not be infectious in origin. Obviously, we know to avoid anything that might cause the above.

I think we can divide our interventions into two types:

a. those that inherently disrupt the glycocalyx –

b. those that secondarily disrupt it via another mediator – eg over-resuscitation and ANP/BNP (John’s “evil twins”) elevation causing breakdown.

Here are some interesting facts, in no particular order of importance:

a. in acute hyperglycemia and in type I diabetes, there is significant loss of glycocalyx volume.

Nieuwdorp M, van Haeften TW, Gouverneur MC, Mooij HL, van Lieshout MH, Levi M, Meijers JC, Holleman F, Hoekstra JB, Vink H, Kastelein JJ, Stroes ES (2006) Loss of endothelial glycocalyx during acute hyperglycemia coincides with endothelial dysfunction and coagulation activation in vivo. Diabetes 55:480–486.

Nieuwdorp M, Mooij HL, Kroon J, Atasever B, Spaan JA, Ince C, Holleman F, Diamant M, Heine RJ, Hoekstra JB, Kastelein JJ, Stroes ES, Vink H (2006) Endothelial glycocalyx damage coincides with microalbuminuria in type 1 diabetes. Diabetes 55:1127–1132

b. high fat/high cholesterol diet and high LDL levels disrupt the glycocalyx. The co-infusion of superoxide dysmutase and catalase with ox-LDL abolishes the glycocalyx shedding found with ox-LDL infusion only. (not exactly a big surprise, but certainly brings up a therapeutic possibility in acute coronary events, especially NSTEMIs…)

Vink H, Constantinescu AA, Spaan JA (2000) Oxidized lipoproteins degrade the endothelial surface layer: implications for platelet–endothelial cell adhesion. Circulation 101:1500–1502

van den Berg BM, Spaan JA, Rolf TM, Vink H (2006) Atherogenic region and diet diminish glycocalyx dimension and increase intima-to-media ratios at murine carotid artery bifurcation. Am J Physiol Heart Circ Physiol 290:H915–H920

c. hydrocortisone and antithrombin prevent TNF-a induced shedding of the glycocalyx. (we never really knew how steroids help in sepsis; ATIII trials failed, but were they designed with glycocalyx-sparing in mind…?)

Daniel Chappell MD, Klaus Hofmann-Kiefer, Matthias Jacob, Markus Rehm, Josef Briegel, Ulrich Welsch, Peter Conzen, Bernhard F. Becker TNF-α induced shedding of the endothelial glycocalyx is prevented by hydrocortisone and antithrombin Basic Research in Cardiology, January 2009, Volume 104, Issue 1, pp 78-89

 d. endotoxemia damages the pulmonary vascular endothelium and results in ALI (now the neutrophils can attach and activate inflammation…)

Eric P Schmidt, Yimu Yang, William J Janssen, Aneta Gandjeva, Mario J Perez, Lea Barthel, Rachel L Zemans, Joel C Bowman, Dan E Koyanagi, Zulma X Yunt, Lynelle P Smith, Sara S Cheng, Katherine H Overdier, Kathy R Thompson, Mark W Geraci, Ivor S Douglas, David B Pearse & Rubin M Tuder The pulmonary endothelial glycocalyx regulates neutrophil adhesion and lung injury during experimental sepsis, Nature Medicine 18,1217–1223 (2012)

e. sepsis and major abdominal surgery damage the glycocalyx (a good example of common pathway pathophysiology…)

Jochen Steppan, M.D., Stefan Hofer, M.D., Benjamin Funke, M.D., Thorsten Brenner, M.D., Michael Henrich, M.D., Ph.D., Eike Martin, M.D.,Jürgen Weitz, M.D., Ursula Hofmann, M.D., Markus A. Weigand, M.D.Sepsis and Major Abdominal Surgery Lead to Flaking of the Endothelial Glycocalix Journal of Surgical Research Volume 165, Issue 1 ,Pages 136-141, January 2011

f. molecules (eg Slit2N,  good old aPC) that enhance or preserve barrier function have shown some success in animal models. (the key might be to using a bunch of them at once, not one of them vs placebo)

N. R. London, W. Zhu, F. A. Bozza, M. C. Smith, D. M. Greif, L. K. Sorensen, L. Chen, Y. Kaminoh, A. C. Chan, S. F. Passi, C. W. Day, D. L. Barnard, G. A. Zimmerman, M. A. Krasnow, D. Y. Li, Targeting Robo4-dependent Slit signaling to survive the cytokine storm in sepsis and infl uenza. Sci. Transl. Med. 2, 23ra19 (2010).

…and this is just the tip of the iceberg. Seriously, google it…

Conclusion:

For now, it is difficult to make any hard recommendations, but it has certainly made me pause to regroup and re-strategize. I think the critical thing is to reframe our thinking and redesign our approach to be a glycocalyx-sparing therapy.

In sepsis therapy, so many molecules have failed, but little emphasis so far has been on targeting the glycocalyx, and in all likelihood, the key is not in finding the “magic bullet” but rather using multiple interventions to bolster it. One could think of this as the sepsis “chain-of-survival”, and now that we can see the complexity of the glycocalyx, it is easy to understand how no one therapy, even if it did do its job, would succeed in preventing the degradation of the other links in the chain, and fail.  In all likelihood, a successful strategy will probably involve the following:

1. fancy molecules to prevent glycocalyx damage.

2. fluid choices which are glycocalyx-friendly.

3. fluid in just the right amount (not by macro/volume-responsiveness but by micro/glycocalyx management).

4. rapid diagnosis/abx/source control, etc, all the good stuff we know about.

5. preventing hyperglycemia.

A trial like that would be a monumental undertaking. I can only hope someone does it.

My next step, as a guy in the bedside trenches and not at the bench, after gaining a modicum of understanding on the topic, will be to delve deeper into the effects of currently available fluids on the glycocalyx.  Look for a post on that in the next weeks.  As a starter, everyone should review Woodcock & Woodcock’s excellent clinical review.

And if anyone has any amazing information to share, please do!!! That’s what #FOAMed is for!!!

Suggested viewing/reading:

Woodcock and Woodcock, BJA 2012,  http://bja.oxfordjournals.org/content/early/2012/01/29/bja.aer515.full.pdf+html

Broken Barriers: A New Take on Sepsis Pathogenesis Neil M. Goldenberg,1* Benjamin E. Steinberg,1* Arthur S. Slutsky,2,3,4 Warren L. Lee2,4 Science Translational Medicine, 22 June 2011 Vol 3 Issue 88 88ps25

Click to access Science_Translational_Medicine_2011_Pathogenesis_of_Sepsis.pdf

a great article on understanding the glycocalyx in sepsis by a U of T gang!

emcrit:

http://emcrit.org/blogpost/best-fluids-comment-ever/

http://emcrit.org/podcasts/fluids-severe-sepsis/

http://emcrit.org/podcasts/paul-marik-fluids-sepsis/

all must-listen/watch material!

other refs.

Luft JH (1966) Fine structures of capillary and endocapillary layer as revealed by ruthenium red. Fed Proc 25:1773-1783

Reitsma et al, The endothelial glycocalyx: composition, functions, and visualization, Eur J Physiol (2007) 454:345–359

Zhang X, Adamson RH, Curry FR, Weinbaum S (2006) A 1-D model to explore the effects of tissue loading and tissue concentration gradients in the revised Starling principle. Am J Physiol Heart Circ Physiol 291:H2950–H2964

A Paradigm shift: re-thinking sepsis, and maybe shock in general… #FOAMed, #FOAMcc

Thomas Kuhn, physicist and philosopher, in his groundbreaking and science changing text, The Structure of Scientific Revolutions, states that:

“Successive transition from one paradigm to another via revolution is the usual developmental pattern of a mature science.”

In other words, a science has growing pains and is bound to have a fair bit of debate and controversy, until a new paradigm becomes dominant.  I think that there is a current – in part prompted by the power of socio-professional media which has allowed minds to connect and knowledge to spread – that will see many of the things that are now “Standard of Care” out the door.

So first of all, the following are must-listens, the first a lecture by Paul Marik, whom I have had the chance to collaborate with in the last years and respect greatly, on knowledge, experience, and even more on his refusal to take anything for granted and being in a seemingly-constant quest for the improvement of medicine.

The second link is Scott Weingart’s take on it, which I think is equally awesome.

I think Paul is pushing the envelope in an essential way, and Scott does a fantastic job of seeing or putting it in perspective. Enjoy:

http://emcrit.org/podcasts/paul-marik-fluids-sepsis/

EMCrit 112 – A Response to the Marik Sepsis Fluids Lecture

My (very) humble opinion on this is a rather simple, almost philosophical one:  why are we seemingly obsessed with treating a predominantly vasodilatory pathology with large amounts of volume?  I’ve said this in previous posts and podcasts, but this, in my opinion, is largely cultural and dogmatic. “Levophed – Leave’em dead” is something I heard as a student and resident, and came to take for granted that I should give lots of fluid in hopes of avoiding pressors… But there’s no evidence at all to support this.  The common behavior of waiting until someone has clearly failed volume resuscitation before starting pressors befuddles me (think how long it takes to get two liters of fluid in most ERs…).  If I was in that bed, I’d much rather spend an hour a bit “hypertensive” (eg with a MAP above 70) than a bit hypotensive while awaiting final confirmation that I do, in fact, need pressors.

I strongly suspect that it’s just a matter of improving vascular tone, giving some volume (which may be that 3 liter mark), and ensuring that the microcirculation/glycocalyx is as undisturbed as possible. Now when I say it may be the 3 liters, I firmly believe this will not apply to everyone, and that it will be 1 liter in some, and 4 in others, and that a recipe approach will be better than nothing, but likely harm some.

I think that blind (eg no echo assessment) of shock is absurd, and for anyone to propose an algorithm that does not include point-of-care ultrasound is only acceptable if they are in the process of acquiring the skill with the intention of modifying their approach in the very near future.

The whole microcirculation/glycocalyx is absolutely fascinating stuff, and undoubtedly will come under scrutiny in the next few years, and it is definitely something I will focus on in upcoming posts & podcasts. Our resuscitation has been macro-focused, and certainly it is time to take a look at the little guys, who might turn out to have most of the answers. For instance, there is some remarkable data on HDAC inhibitors (common valproic acid) and their salutatory effects in a number of acute conditions such as hemorrhagic shock (Dr. Alam) which have nothing to do with macro-resuscitation, and everything to do with cell signaling and apoptosis. Hmmm…

please share your thoughts!

thanks

Philippe

Bedside Ultrasound: The Sluggish IVC – something to look for… #FOAMed, #FOAMcc

So take a look at this:

I’m sure most experienced bedside sonographers come across this all the time.  For those who are starting out, and until now have just been looking at size and variation, take a second to look at the flow.  You can actually see the flow stop and start, which tells you your cardiac output is bad.  It could be bad because of the RV, the LV, the pericardium, the tension pneumothorax, anything, but it’s bad.  So just in case you were only gonna look at the IVC, keep looking! You will find something abnormal downstream, perhaps that you can do something about (not fluids, though).

I have seen this disappear and clear up with – when possible – correction of the problem, back to the normally anechoic IVC we usually see.

thanks!

Philippe

ps note there is also a mirror artifact in the right lower portion of the field, making it look as though there are two beating hearts.

Beta-blockers in Sepsis? Interesting… #FOAMed, #FOAMcc

Very interesting article in JAMA: http://jama.jamanetwork.com/article.aspx?articleID=1752246

I’m curious as to whether this has been generating interest in the cc community.  I think it is one of those articles that – at least conceptually – shines light in an area we don’t spend much time reflecting on.

I know that as an IM resident, and a CC fellow, my understanding of vasopressor therapy was pretty basic: squeeze the vessels to bring up the pressure, and hope you don’t squeeze so hard the fingers and toes fall off. In truth, no one ever really pointed out that to some degree or other, the same process killing off the fingers is probably happening to a varying degree in all organs. But maybe I just nodded off and missed it.

Since then, however, I’ve had some time to  re-examine things, and my practice has slowly been evolving.  For one thing, bedside ultrasound allows a really good assessment of inotropy, so I started to ask myself why I was giving b-agonists to patients who clearly didn’t need any help with contractility (e.g. normal, and even more so, hyperdynamic RVs and LVs).  After all, I’m putting them at risk for arrhythmias, or at least tachycardia. So whereas levophed (norepinephrine) remains my reflex pressor, I routinely shift to phenylephrine when faced with arrhythmias (most commonly fast atrial fibrillation) or tachycardia (beyond 110-120) once adequate volume resuscitation has been done.  Why 110-120?  Its an absolute guess. Somewhat educated – or I try to convince myself of that – in figuring that at some point, the increased CO via HR will be offset by decreased filling time, and with the weak but recurring data showing an association between tachycardia over 90-100 and poor outcome.

So this study – counterintuitive as it may sound to some – is really about blunting the potentially unwanted effects of b-agonists.  They randomised 336 patients to IV esmolol to a HR <95 vs a control group of standard care. They found a reduced mortality of 60%… Obviously the massive benefit should be taken with a healthy dose of skepticism, but even just the fact that they didn’t make patients worse is very, very significant.

Read the paper. They do a great job of reviewing the concept and it’s worth going over their protocol.

Physiologically, we know that catecholamines can cause stress cardiomyopathy.  The question is, when cardiomyopathy is noted, how often do we think this is related to therapy?  More often, we figure it’s the disease process – septic cardiomyopathy. At the bedside, this is impossible to differentiate.

The concept of lusitropy – active relaxation – and its contribution to cardiac output – is often overlooked, and can be affected by catecholamines. In fact it can be the most important factor related to preload, despite getting much less attention than volume loading. Remember that preload is not a pressure (especially not a CVP!!!), but a volume, and physiologically it is the degree of myocardial stretch. The ventricle is not passive, and its compliance is highly related to the active relaxation phase. Fluids will not affect this.

In addition, the decreased filling time by tachycardia can also decrease output.

Fantastic study, even if only to open the door.  I would have liked (in typical N=1 fashion and as a bedside sonographer) to see a quick echo prior to initiation, and seeing if there would have been an association with baseline RV/LV function and response/outcome to esmolol. Intuitively and physiologically, it would seem that the hyperdynamic RVs and LVs would have benefitted most, since they didn’t need beta agonism to start with – but I can also entertain that those would be unaffected and that the worse ventricles could have been worsened by stress cardiomyopathy… So a critical question in my opinion.

So…bottom line?  Is this practice-changing? It might be.  For me, I might start looking at RV/LV and opting for a quicker conversion to neosynephrine if I see a hyperdynamic state or lowering my HR threshold to do so…100? 105? – maybe just a shift rather than a change in practice. I’m not sure I’ll start esmolol infusions yet, but it will be at the back of my mind and I might, given the right set of circumstances. What I would like to see is reproducibility, and if it does happen, I would be happy to get HR’s under 95.

Love to hear what anyone else has to say!


Philippe


NEJM Circulatory Shock Review by Vincent & DeBacker: the sweet and the not-so sweet… #FOAMed, #FOAMcc

So if anyone hasn’t read it, here it is:

Click to access Circulatory%20Shock%20-%20NEJM%202013.pdf

I read the article by critical care icons Dr. Jean-Louis Vincent and Dr. De Backer with interest  as I am always keen to find out what the cutting edge is… So here is my take on their review.

The not-so-sweet:

The inclusion of CVP in the assessment. Ouch. No evidence whatsoever. Evidence for lack of correlation to fluid responsiveness… I wonder if they themselves were cringing a little about including it, particularly form the fact that they just put high vs low rather than commit to a value, which makes me think they realize it’s a bit of a trap. (It reminds me a bit of those night-time orders I still sometimes see which say if u/o < 30 cc/hr give a bolus if CVP under 12 or lasix if over 12.  So basically depending on whether that patient’s head is elevated, or if he’s turned on one side or the other, he may go from “needing fluids” to “needing diuretics”…).

The sweet:

First of all, they obviously did an elegant job on description of shock states, and particularly of highlighting the common-ness of mixed etiology shock.

I like that they admitted that the end-point for fluid resuscitation is “difficult to define.”  Any answer other than that would really speak to non-physiological thinking, as I’ve referred to in prior posts/podcasts.

Dopamine: good job on trying to take it off the shelf for shock. As far as I’m concerned, only useful when you’ve run out of norepinephrine, although there is the odd time when you have a septic AND bradycardic patient where it could come in handy…

Bringing some focus on the microcirculation: no recommendations, but that’s appropriate since there are none to be made yet, but this is where the money is in the future, as far as I’m concerned. Once we figure out how to manage the microcirculation (we do ok with the macro circulation) we might forge ahead. But good to point the finger in that direction.

The super-sweet!

I do (not surprisingly) really, really like the fact that they included ultrasound in their assessment protocol, and emphasizing that focused echocardiography should be done as soon as possible.  Very nice. Finally.

Hopefully, this pushes mainstream ED and critical care physicians to realize they need basic bedside ultrasound skills…


Overall, I think it is a good review, certainly worth the read for trainees. I would like to see focus on re-examining and questioning our approach, which could spur readers to embark on research with a different angle. For instance, why do we assume that we need to fill patients to the point of no longer being fluid responsive in order to avoid vasopressors? Is there any evidence for that? Not that I know of…

But, for having put an emphasis on point-of-care ultrasound, it gets a big round of applause from me!


Philippe

Bedside Ultrasound Picture Quiz 2 #FOAMed, #FOAMcc

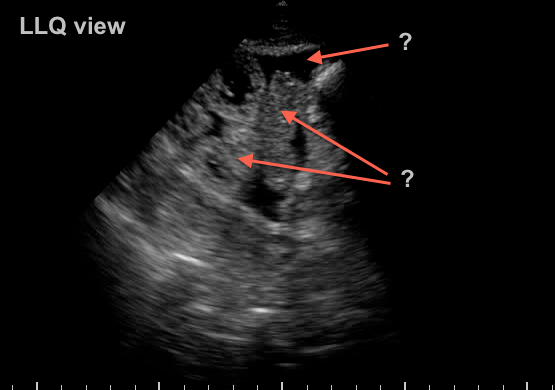
73 yr old woman recovering from septic shock with abdominal distension and difficulty tolerating enteral feeds…


what do you see?

BUPQ2


scroll below for the answer…..


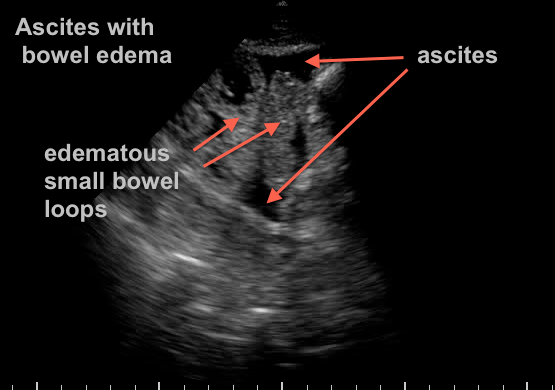
BUPQ2 Answer


Extensive third spacing from resuscitation has resulted in bowel edema and ascites.  Another “benign” effect of massive crystalloid use… A bedside 22g US guided tap confirms benign transudate.

How much fluid should I give? #FOAMed, #FOAMcc

I’m putting this question out there so that everyone can reach into their bag of tricks and tell me “this is how I know how much to give.”  Because I really do want to know.

To the best of my knowledge, that answer does not exist.

Of course, someone can say “we have to give 2 liters of crystalloids!” loudly and clearly, raising a fistful of papers and guidelines where it is printed, black on white.

Now lets think about exactly what that question is really asking, which is: how much fluid can I safely give my patient to improve the hemodynamic status without a significant cost in terms of complications, both short and long-term?

What are the implications of this statement?

a. My patient must be volume responsive.

b. I must not cross the threshold of excessive fluid administration. 

c. I must KNOW that fluid loading is the most appropriate therapy for my patient.

Now when you start looking at those questions and really wondering whether you have a definite answer for all of them, if becomes quite difficult.  It is much easier to say “well, such-and-such study says people do better if I give them x amount.”  This is probably true, that most people do better with a certain amount of fluid. But not everyone, because there are a lot of variables within those three questions.

Lets go through these questions:

My patient must be volume responsive – this is worth an entire podcast/lecture/article and there are a number of technologies and techniques out there which have both physiological and practical merit. I’ll get into that soon, but the short answer is that a passive leg raise (PLR) coupled with good cardiac output monitoring would be the “gold medal,” bedside ultrasound of the IVC’s global dynamics would be the “silver medal” and most of the rest would be “bronze medal” material at best. I won’t even mention the traditional physical exam or history or labs, not only do they not make it onto the podium, they didn’t make it into the stadium. I have to thank Scott Weingart (www.emcrit.org) for the sports analogy which I think is really excellent, since making the podium is actually pretty good and the difference between the three medalists may not always be that great.

I must not cross the threshold of excessive fluid administration – this one is dicey, because that’s where you have to factor in the patient’s oncotic pressure, hydrostatic pressure, both of which can be somewhat estimated, but mostly the degree of leak or “capillaritis”, both systemic and local, and that, at initial presentation, is impossible. The best you can do is a very broad classification from not too leaky to really, really leaky. And that’s not science. Now my good and highly esteemed friend Daniel Lichtenstein (the true founder of bedside ultrasound) published the FALLS Protocol, which basically says you can fill someone up until the appearance of B lines (during resuscitation) by lung ultrasound is certainly right that you should stop at this point, but I would contend you probably need to stop a bit before the edema is actually happening, especially since, in all likelihood and especially with crystalloids, the extravasation will continue for a while. The SOAP and VASST studies clearly showed an association between positive fluid balance and mortality, all other factors adjusted. Hence, this question is almost impossible to answer with knowledge. An educated guess is the best we can hope for.

I must KNOW that fluid loading is the most appropriate therapy for my patient – now this is almost philosophical and anxiety-arousing, because it forces us to challenge the fundamentals of our therapy. In certain cases, it is quite clear. If someone has been hemorrhaging or overdiuresed into shock, it is fair to say that you know they need fluids. However, if we are dealing with a vasodilatory circulatory failure, why do we feel compelled to treat it with a therapy best reserved for hypovolemic circulatory failure…  Hmmm. Food for thought. Perhaps we can start by looking back and seeing what the basis is for our almost unshakeable beliefs that fluids are benign and that vasoactive medications are evil… But that is for the near future.

Please, let me know what you think. I hope someone disagrees strongly.


Philippe Rola

http://www.ccusinstitute.org